Introduction
Indications
Benefits and disadvantages
Contraindications and precautions
Mechanism and dose
Initiation, discontinuation and monitoring
Side effects, risks and drug interactions
Azathioprine is an antimetabolite prodrug prescribed to suppress the immune system of individuals with inflammatory disease.
Azathioprine is first metabolised to mercaptopurine (or 6-mercaptopurine; 6-MP), which is in turn metabolised to the active compound, thioguanine. Thioguanine is a purine analogue that is incorporated as a dysfunctional nucleotide into the DNA/RNA of T and B cells. This disrupts the capacity for T and B cells to proliferate and synthesise effector proteins including cytokines and immunoglobulins.
Azathioprine, mercaptopurine, and thioguanine are all thiopurine-class purine antimetabolite medications available for standalone prescription. However, azathioprine is more frequently used in clinical practice due to a well-established evidence base, and favourable pharmacodynamics through conversion from prodrug to active metabolite.
Dermatological indications of azathioprine include:
Off-label use as an immunomodulatory, steroid-sparing agent with good evidence in:
Other non-dermatology indications:
Azathioprine and its metabolites are considered Category D in pregnancy indicating ‘may be expected to cause an increased incidence of human fetal malformations or irreversible damage’. Individuals exposed to azathioprine in pregnancy can be advised that no teratogenic nor harmful signals were detected within small cohorts receiving 50-250mg daily. However, the antimetabolite mechanism that disrupts DNA and RNA replication should warrant a high degree of caution.
The benefits of breastfeeding are considered to outweigh risks of infant exposure to azathioprine through breastmilk. Azathioprine has very low excretion in breastmilk that peaks 1-2 hours after medication administration. Infant exposure can be minimised by breastfeeding four hours after taking azathioprine.
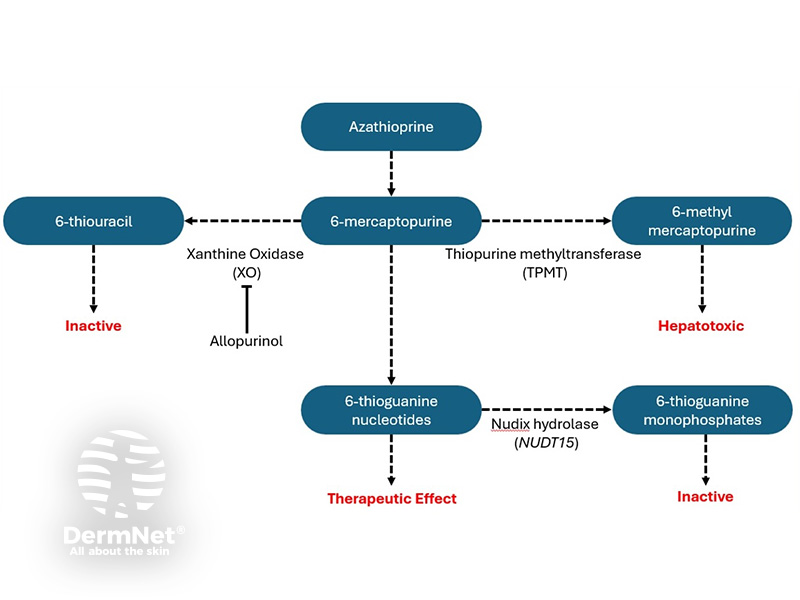
Azathioprine is a prodrug that is metabolised first to mercaptopurine, and next to the active metabolite, thioguanine. This is supported by evidence that clinical response to azathioprine is correlated to therapeutic drug levels of thioguanine but not mercaptopurine.
Thioguanine is an antimetabolite that is incorporated into replicating DNA/RNA as a dysfunctional nucleotide in the place of purines bases (adenosine, guanine). Inclusion of the dysfunctional nucleotide disrupts cell proliferation and protein production. This mechanism disproportionately affects T and B lymphocytes that execute their immune function through proliferation and synthesis of effector cytokine and immunoglobulin proteins.
Azathioprine and mercaptopurine may be available as an oral tablet, oral liquid, rectal foam, or intravenous injection.
The dose of azathioprine is generally 1–3 mg/kg/day, however the individualised dose is dependent on several factors including indication, age, response, and individual pharmacokinetics. Dose reduction may be required given that azathioprine and its metabolites are hepatically converted and renally excreted.
Effects of azathioprine and mercaptopurine may take up to several months to be seen — this should be considered when reviewing the dose.
The clinical efficacy and safety of azathioprine is dependent on a complex metabolic pathway. Testing for key components of this metabolic pathway may personalise dosing to ensure therapeutic drug levels and avoid toxicity.
Best practice requires pre-screening of the enzyme thiopurine methyltransferase (TPMT) that converts mercaptopurine to methyl mercaptopurine. Decreased TPMT activity will shunt metabolism towards the active thioguanine metabolite risking supratherapeutic levels and myelosuppression. Approximately 10% of patients will have intermediate-low TMPT activity and less than 1% will have absent TPMT.
Supratherapeutic and toxic thioguanine levels may result from decreased activity of the nudix hydrolase enzyme that functions to inactivate thioguanine. This enzyme is influenced by genetic polymorphisms at the NUDT15 allele that are primarily detected in East Asian individuals causing intermediate-low function in 21% and absent function in 2% of individuals.
Subtherapeutic thioguanine levels may result from increased activity of the xanthine oxidate enzyme that shunts mercaptopurine metabolism towards the inactive thiouracil metabolite. High xanthine oxidase activity can be inferred from therapeutic drug monitoring that shows an increased ratio of mercaptopurine to thioguanine. Allopurinol is an inhibitor of xanthine oxidase that can be prescribed at low dose to correct metabolism towards the active thioguanine metabolite.
Figure 1: Azathioprine, mercaptopurine, and thioguanine metabolism
Before starting treatment:
During treatment:
Azathioprine should be stopped and promptly managed jointly with a haematologist if:
Azathioprine and mercaptopurine usually cause mild side effects but may occasionally be severe enough to stop treatment.
Common side effects include:
Uncommon side effects include:
Severe adverse effects include:
Azathioprine hypersensitivity syndrome
If the use of an interacting drug combination is unavoidable, dose adjustment may be required and blood counts should be monitored carefully. Interactions include: