Lesions (cancerous) Diagnosis and testing
Last Reviewed: October, 2026
Introduction - cutaneous squamous cell carcinoma
Introduction - skin of colour
Demographics
Causes
Clinical features
Complications
Diagnosis
Differential diagnoses
Treatment
Prevention
Outcome
Cutaneous squamous cell carcinoma (cSCC) is a common malignant tumour arising from keratinocytes of the epidermis or hair follicle epithelium. It invades surrounding tissue and has the potential to metastasise.
Cutaneous SCC in skin of colour differs in risk factors, site, and prognosis compared to presentations in white skin.
‘Skin of colour’ is an imprecise term encompassing skin with more constitutive melanin pigmentation than white skin, often corresponding to a Fitzpatrick skin phototype IV or higher. In some contexts, it is a proxy for people from non-White ethnic groups, including those of African, Asian, Hispanic/Latino, Pacific Islander, Māori, and Middle Eastern descent.
Ultimately, ‘skin of colour’ is not a biological category, nor is it interchangeable with race, ethnicity, or Fitzpatrick skin phototyping. See ethnic dermatology for more information.
Cutaneous squamous cell carcinoma is among the most commonly diagnosed cancers worldwide, accounting for 15–25% of all diagnosed skin cancers:
The highest rates of cSCC occur in white-skinned individuals. Conversely, reported rates are low among those with darkly pigmented skin.
Across all skin types, cSCC incidence is greater in:
More than 90% of cutaneous squamous cell carcinoma cases are associated with numerous DNA mutations in multiple somatic genes.
In those with darkly pigmented skin, ultraviolet radiation-induced damage to keratinocyte DNA is not considered a prominent driver of cSCC development. By contrast, UVR exposure is a major risk factor in individuals with white skin.
While higher amounts of constitutional eumelanin reduce the risk of cSCC, the risk is not entirely eliminated.
Important risk factors for cSCC development in skin of colour include:
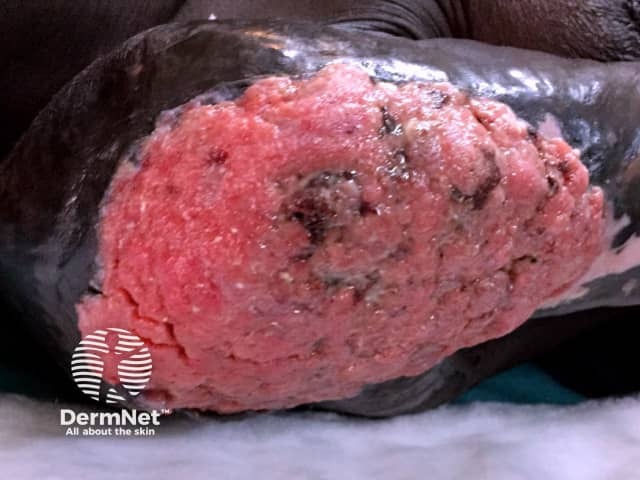


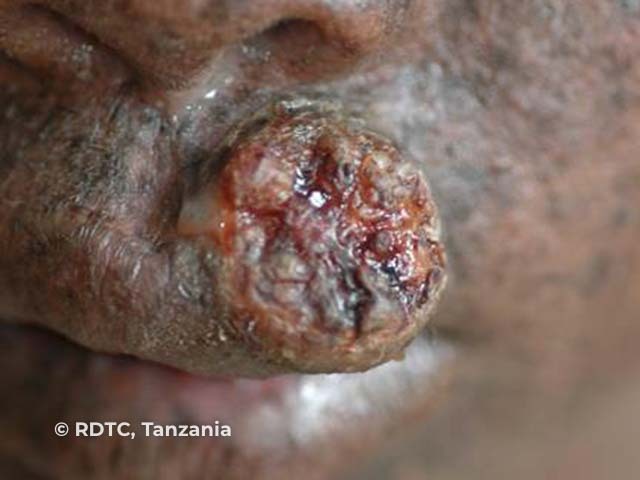
The presentation of cutaneous squamous cell carcinoma varies by the histologic subtype and location.
In people with lightly pigmented skin, lesions typically appear on frequently sun-exposed sites, with most arising from a preinvasive or in-situ tumour eg, actinic keratosis or Bowen disease.
By contrast, cutaneous SCCs in people with darkly pigmented skin are more likely to arise on sun-protected sites (including the lower limbs, feet, and anogenital region), particularly within chronic inflammatory or scarring processes.
General clinical features:
High-risk features of cutaneous squamous cell carcinoma:
For more information on subtypes and staging, see: cutaneous squamous cell carcinoma
Complications of untreated or advanced cSCC include local tissue or nerve damage, treatment-related complications, metastasis, and ultimately death.
In skin of colour, cSCC is more likely to arise on photoprotected sites and/or within chronic scarring or inflammatory processes:
Cutaneous squamous cell carcinoma is usually suspected during a physical examination, often with the aid of a dermatoscope. In skin of colour, special attention may need to be given to areas not typically exposed to the sun and those that are scarred or chronically inflamed.
Diagnosis is confirmed by histopathological examination (see: squamous cell carcinoma pathology). Depending on the lesion’s site, size, and suspected depth, an appropriately deep shave, punch, incisional or excisional biopsy may be performed.
High-risk or advanced SCC may require imaging and regional lymph node assessment to determine the extent of the disease.
Staging depends on the tumour site and characteristics. For information on staging, see: cutaneous squamous cell carcinoma.
Surgical excision is the recommended first-line treatment, regardless of skin colour. Margin selection depends on tumour risk, site, and pathological features.
Recommendations for excision margins are as follows:
Mohs micrographic surgery is recommended for large facial lesions with indistinct margins or for recurrent tumours. (For more information on treatment, see: cutaneous squamous cell carcinoma)
Follow-up should be individualised according to the risk of recurrence, metastasis, and development of additional SCCs. People at high risk may require more frequent clinical review.
Although the association between UV exposure and SCC is weaker in people with skin of colour, sun protection remains appropriate, particularly for people with additional risk factors such as immunosuppression, previous SCC, or actinic damage.
Sun protection methods include:
Regular self-skin examination is particularly important because SCC may arise in sun-protected areas or within chronic scars and inflammatory skin disease.
Systemic retinoids such as acitretin may be considered by a specialist for selected patients at very high risk of multiple cutaneous SCCs, particularly solid-organ transplant recipients. Adverse effects can be disruptive, and acitretin is strongly teratogenic and contraindicated in pregnancy.
Cutaneous squamous cell carcinoma generally has a good prognosis, with most SCCs successfully treated. Poor prognostic factors include greater tumour diameter and depth of invasion, poor differentiation, perineural invasion, immunosuppression, recurrence, and regional or distant metastasis.
Some populations with skin of colour present with more advanced disease, but this should not be attributed to pigmentation alone. Tumour site, chronic scarring, chronic inflammation, delayed diagnosis, access to care, and underrepresentation of people with skin of colour in clinical research may all contribute to this disparity.